

By Subrat Bahinipati, PT, Physical therapist and co-founder, Synergy Therapeutic Group, Carbondale, Illinois · 30+ years treating chronic and complex pain
Clinically reviewed by Subrat Bahinipati, PT on · Last updated
Key Takeaways
- A headache that begins at the base of the skull may be driven or worsened by a problem in the neck. But the region involved is often larger than the neck alone.
- At Synergy, we look at the entire upper quadrant: the upper back, shoulder blades, shoulders, neck, jaw and base of the skull. These areas work together. They should not automatically be treated as separate problems.
- Pain on one side, reduced neck movement, pain set off by neck position, and pain that travels from the skull toward the forehead all point toward the neck. These findings can overlap with migraine. So the label alone does not tell you what is contributing.
- Headaches usually develop after years of physical adaptation, not one dramatic injury. Pain does not automatically mean the body is damaged or broken.
- Physical-therapy research shows that hands-on treatment and targeted exercise can reduce headache frequency, intensity, disability and medication use. This can hold true even when patients do not fit neatly into one headache type.
Headaches that start in your neck may be cervicogenic, but the diagnostic label is not the whole answer. Migraine, tension-type headache and cervicogenic headache can all occur alongside neck pain. The practical question is simple. Does examining the neck and the area around it bring on your familiar headache? And does treating what we find change it?
In more than three decades of practice, I have repeatedly found that the painful neck is often only one part of the problem. The region involved may include the upper back, shoulder blades, shoulders, jaw, neck and base of the skull. At Synergy, we call this the upper quadrant. When we examine and treat the whole region as one working system, patients may improve even after years of treatment aimed only at the headache or the sorest part of the neck.
What a cervicogenic headache actually is
A cervicogenic headache is a headache whose true source is the joints and muscles of the upper neck, felt in the head because of how the nerves are wired. The top of your neck (the first three vertebrae, C1 through C3) sits right where your skull meets your spine, and the nerves from that region join the nerves that carry sensation to your head at the same relay station in the brainstem. So a headache can result when an upper-neck joint is stiff, irritated or no longer moving normally. It can also happen when the small muscles that hold your head up are overworked. Sensory pathways from the upper neck and the head meet in the nervous system. That is why pain that starts in the neck may be felt in the head.
Think of it like the wiring in an old house. You flip the switch in the hallway and a light comes on in the bedroom, because two circuits were tied together behind the wall. The problem is not the bedroom bulb. Chasing the headache with more headache medicine is like keep-replacing that bedroom bulb. It was never the bulb.
It is usually not just your neck, it is your whole upper quadrant
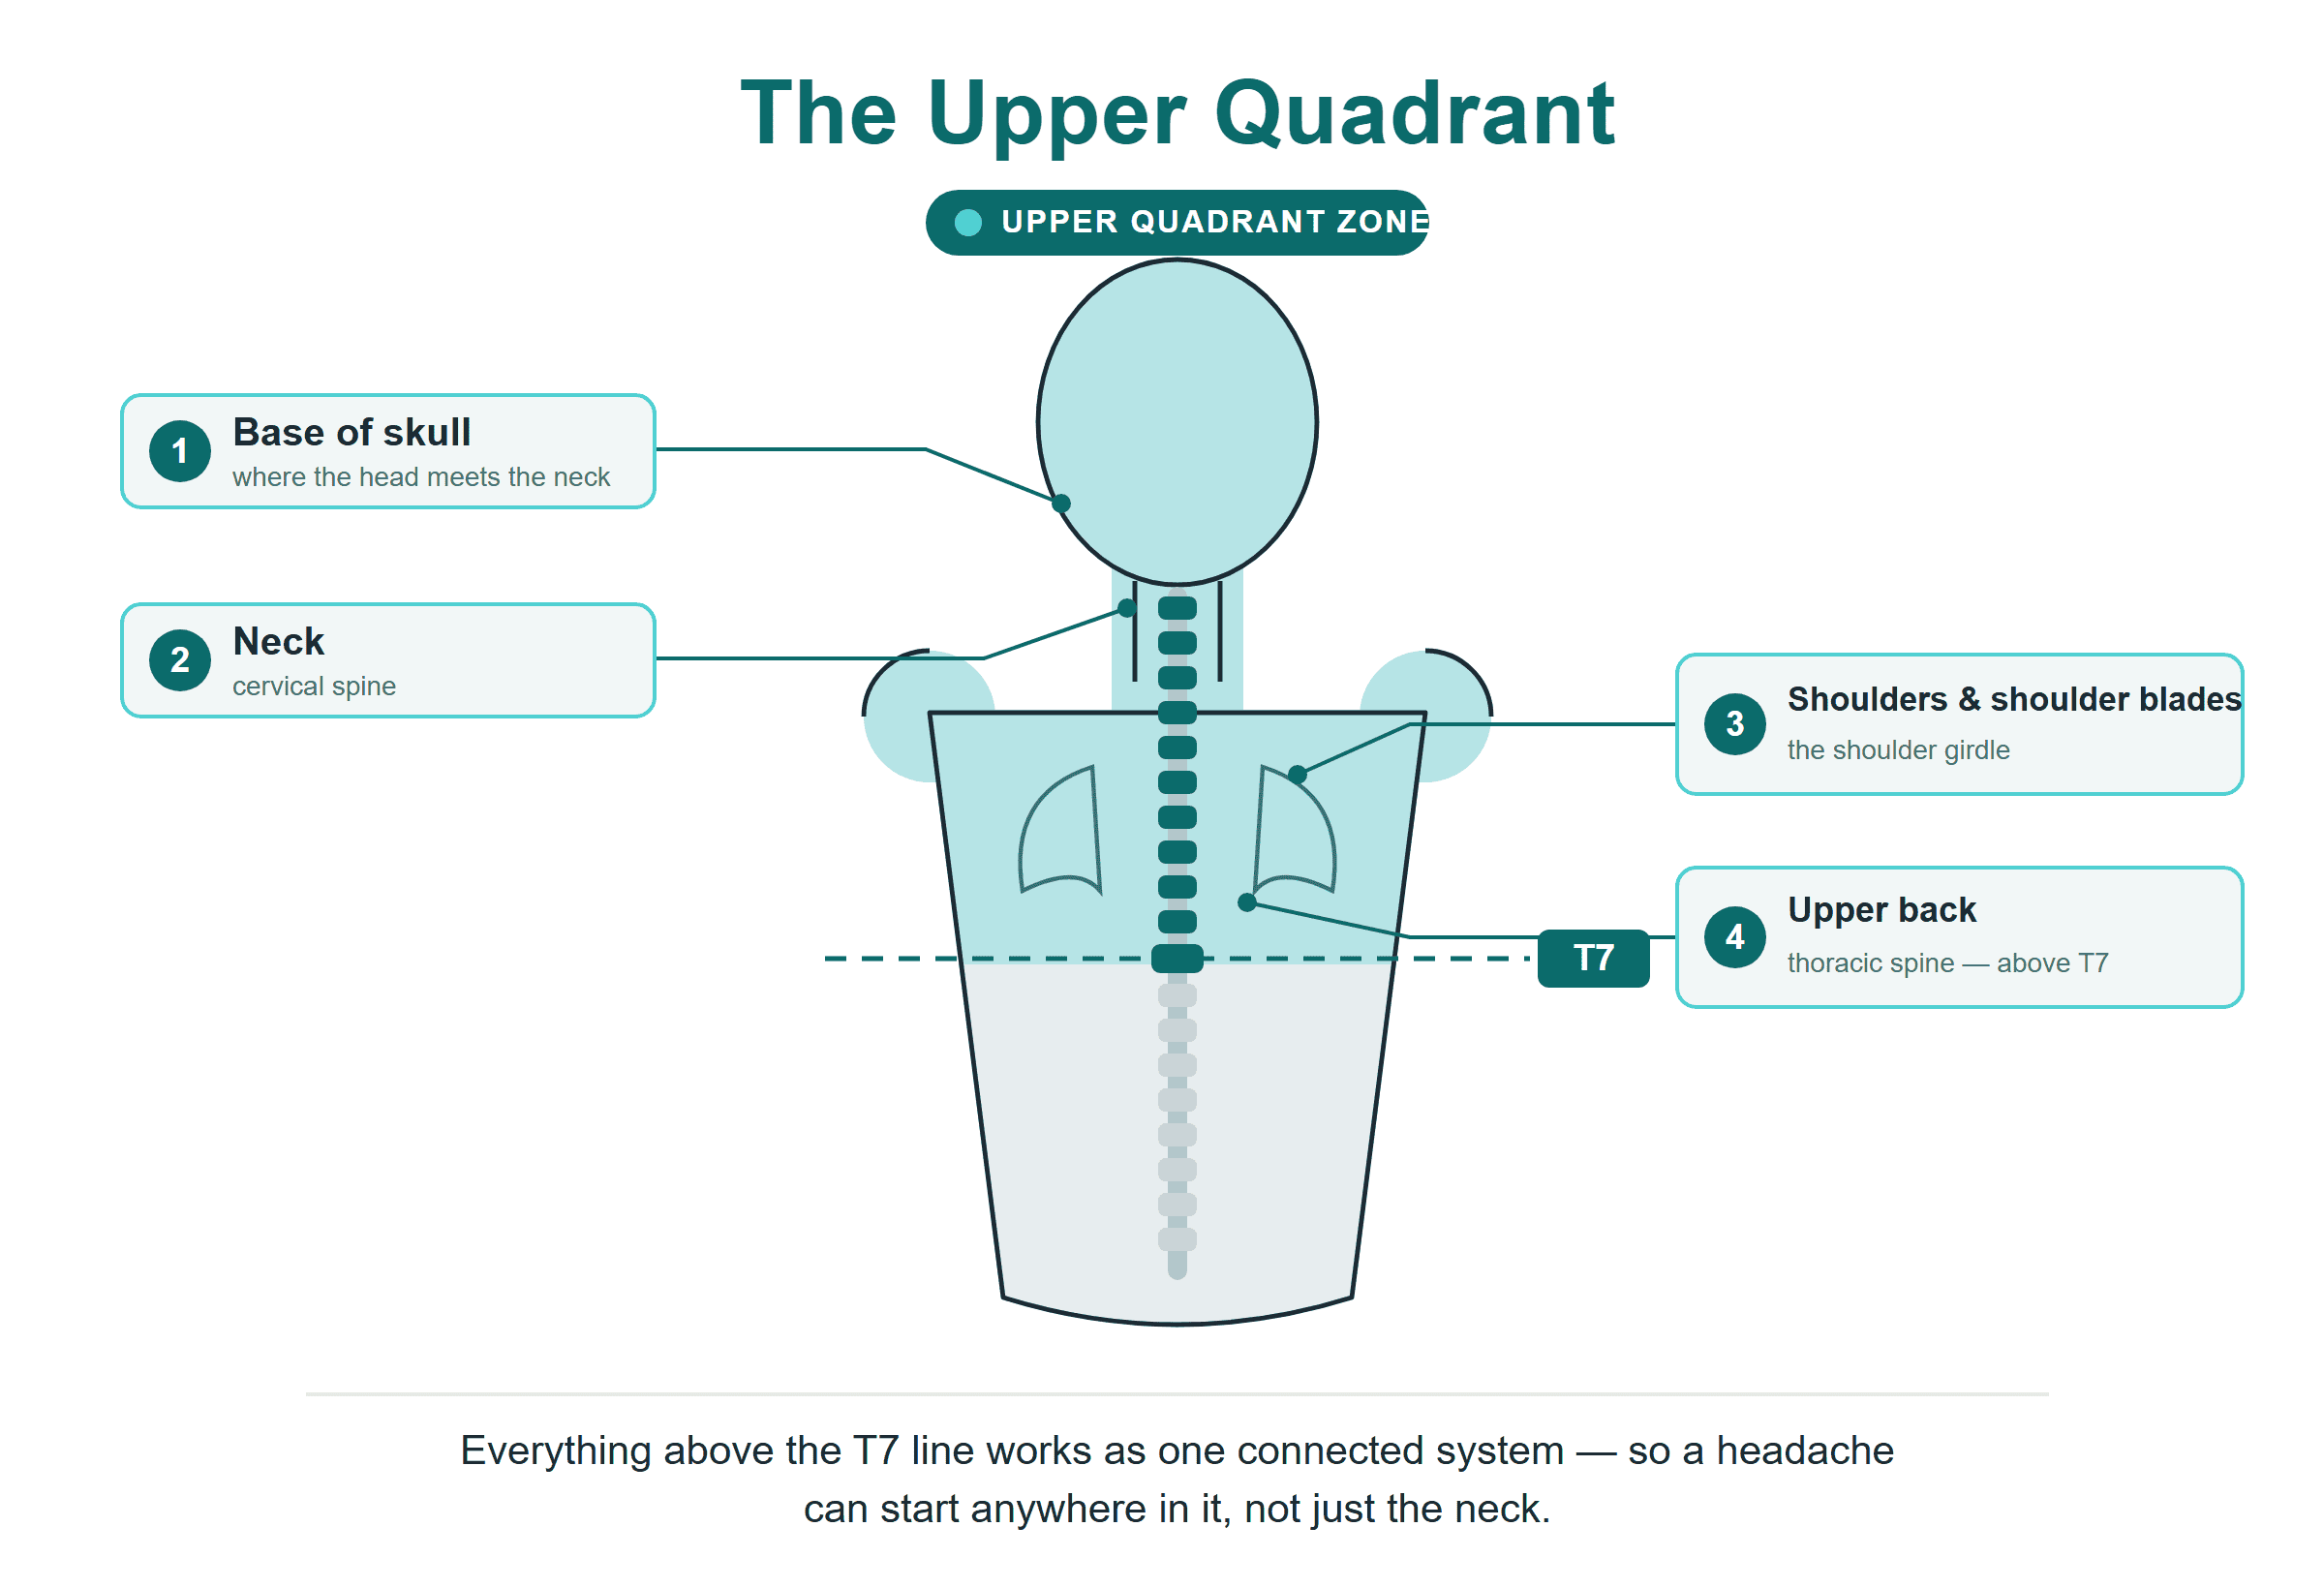
Here is the single idea I most want you to take from this. Picture a horizontal line across your back at about the middle of your shoulder blades. That is the level of the seventh thoracic vertebra, or T7. Everything above that line works together as one connected region. It includes the upper part of your mid-back, your shoulder blades and shoulders, your neck, and the base of your skull. In the clinic we call it the upper quadrant. It is not a collection of separate parts. It is a chain, and every link leans on the others.
This upper-quadrant framework is part of how we evaluate patients at Synergy. It is broader than the usual definition of cervicogenic headache. Research supports examining the upper mid-back, neck joints, muscle performance and shoulder blades. It does not support assuming that the painful spot is the only contributor.
Sometimes one part of that chain gets tight or stops moving well. It might be a stiff upper back from years at a desk, a shoulder that has quietly lost its range, or a rounded posture that pokes the head forward. Then the neck ends up doing more than its share of the work. It is the neck that finally cries out, so the neck gets the blame. But it was often just the weakest link in a region that had been struggling for a long time. That is why loosening only the sore neck gives short-lived relief. If the stiff mid-back and tight shoulders keep dumping load onto the neck, the headache keeps coming back. When an exam shows that several parts of the upper quadrant are contributing, treating only the neck is unlikely to give the best or most lasting result.
How to tell it apart from a migraine or a tension headache
You can usually tell a cervicogenic headache from a migraine by four things. It stays on one side. It is a steady ache rather than a throb. It starts at the base of the skull. And it is set off by neck position. This matters, because the treatment is completely different. A cervicogenic headache has a fairly specific fingerprint. It is usually on one side and tends to stay on that side. It does not usually throb or pulse the way a migraine does. It is more of a steady, deep ache. It often starts at the base of the skull and spreads forward, toward the forehead, temple, or behind one eye. And it is provoked by the neck. Holding your head in one position too long, sleeping wrong, a long drive, or an afternoon hunched over a phone will set it off. Pressing on certain spots at the base of the skull can also reproduce it.
Migraines behave differently. They tend to throb. They often come with strong sensitivity to light and sound, and sometimes with nausea or visual aura. They are driven by their own internal triggers, not by how you are holding your head. The catch is that the two can overlap and can even feed each other. That is exactly why so many neck-driven headaches get filed under “migraine” and treated as if the neck were not there. Not every headache is a migraine. Many of the ones sitting in that folder are coming from the upper quadrant, and nobody has looked.
| Findings suggesting a cervical contribution. | Findings commonly associated with migraine. |
|---|---|
| Familiar headache reproduced by neck movement or pressure. | Moderate or severe headache attacks. |
| Restricted or painful cervical movement. | Nausea or vomiting. |
| Pain frequently begins at the neck or base of the skull. | Marked light or sound sensitivity. |
| Often remains predominantly on one side. | May occur on one or both sides. |
| Upper-back, shoulder, jaw or neck dysfunction may coexist. | Neck pain or stiffness may also be present. |
| Symptoms change when the cervical region is treated. | Symptoms may follow hormonal, sensory, sleep or other triggers. |
These are clues, not an absolute dividing line. Migraine and cervical musculoskeletal dysfunction can exist in the same patient. A person can have a valid migraine diagnosis and still have treatable physical contributors that have never been examined.
Why the neck starts referring pain: your body is changing, not broken
In more than thirty years of treating pain, the biggest misunderstanding I meet is this: people assume pain means something got injured. With these headaches, that is almost never the story. There is rarely one dramatic accident. What there is instead is change. It is slow, steady change in how the body carries itself, stacked up over years until the system finally protests. Your body is not broken. It has been adapting. In many recurring cases, the pain comes from built-up adaptation, a more sensitive nervous system, and changed movement. It is not a sign that the body is permanently damaged.
Picture the load. The average adult head weighs about the same as a bowling ball, balanced on top of a very mobile neck. Tip that head forward to look at a phone or a laptop and the muscles at the base of the skull have to work several times harder to hold it there. Do that for eight hours a day for years. The small suboccipital muscles get tight and cranky. The upper joints stop gliding the way they should. The mid-back stiffens into its rounded shape. The whole upper quadrant slowly reorganizes itself around the position you spend the most time in. The headache is the moment that long, quiet adaptation finally runs out of room.
That is why these headaches so often show up in people who drive for a living, work at a desk, sew, or scroll in bed. It is also why an old whiplash or a long-ago neck injury can come back to haunt you as a headache a decade later. The neck adapted around the old problem, the region above and below it adapted around the neck, and eventually the adaptation ran out of room. Often there is no new tear or single injury that explains why the headache began. The region has slowly changed how it moves, carries load and responds to stress.
How men and women may present differently
Women get headaches more often overall. In my practice, many women with persistent headache also have a lot of upper-quadrant tightness and dysfunction. I have seen fewer men come in mainly for recurring headaches. So a new or unfamiliar headache in a man gets my attention. But this is a clinical observation, not a rule that applies to every patient. A sudden, worsening or very different headache needs proper medical screening in both men and women.
Here is a clinical observation that deserves research. In some women with stubborn headaches, the headache did not fully settle until I found and treated a problem farther down the movement chain, including the pelvis. Direct research has not yet established that pelvic dysfunction causes cervicogenic headache. However, anatomical research supports links through the body’s fascial and movement chains. I am presenting this as a repeated clinical observation from more than thirty years of practice. It is a question that deserves formal study, not a proven explanation.
Why the dominant symptom may change over time
A headache does not literally turn into a jaw or shoulder condition. However, connected parts of the upper quadrant can share mechanical load, muscle guarding and nervous-system sensitivity. As the body keeps adapting, the main symptom may change. The upper quadrant stays tight and overloaded. The body keeps hunting for a way to cope, so the trouble shows up wearing a different costume. The cervicogenic headache that was there last year becomes jaw pain and clicking this year: what people know as TMJ or TMD. Or it becomes a neck that will not turn: “I can’t move my head to check my blind spot anymore.” Or it becomes pain that creeps into the shoulder and down the arm. It “gets better” one week and reappears somewhere new the next. Each new symptom gets its own appointment and its own label, as if they were unrelated. They usually are not. In some patients, they may be different signs of the same overloaded and poorly coordinated region.
The jaw connection in particular (the way an upper-quadrant problem and the jaw feed each other) is a big enough topic that it deserves its own article, and I will give it one soon. For now, the point is simple. Maybe your headaches, your jaw, and your stiff neck have all been treated as separate problems. If so, it is worth asking whether they are really one problem that has been moving around.
What actually settles a neck-driven headache down
Physical therapy research supports treating real physical contributors rather than relying only on the headache label. In a randomized trial of 200 people, manipulative therapy and specific low-load exercise reduced cervicogenic-headache frequency, intensity and neck pain. The benefits were maintained at twelve months. The combination was not significantly better than either treatment alone, but 10% more patients gained relief with it. Another publicly funded randomized trial found that physiotherapy reduced recurring headaches in older adults who had neck pain and cervical dysfunction. This was true even when the patients were not limited to one headache type.
This supports the approach we use at Synergy. We examine what brings on the familiar headache. We restore movement across the upper quadrant. We calm sensitivity and retrain the muscles that manage the region during everyday life. Hands-on treatment can bring relief and restore movement. Individualized exercise helps the body keep and use that change.
One pattern I see repeatedly is a one-sided headache, years of pain pills for short-lived relief, and a fast change once the neck and upper quadrant are actually treated. A real Synergy patient, Susann from Carbondale, came in with exactly that picture. In her own words: “At the beginning of treatment I suffered from severe headaches on the left side. Headaches controlled my life. I took pain pills about 4 times a week but the pain would come back soon. After 1 treatment I felt much better. My headaches disappeared after about 1 hour and overall stayed away. No pain pills taken after treatments have started.”. Susann, Carbondale, IL. You can read how another patient’s stubborn neck, shoulder, and arm pain finally resolved with the same approach, and we cover the link between neck pain and headaches in more detail here.
When to see someone, and who
Your headaches may be one-sided and tied to your neck. If no one has ever actually examined your neck and upper back, that is worth doing. Illinois law allows you to be evaluated by a physical therapist without a physician’s referral. Individual insurance plans may still have authorization or coverage requirements, which our office can help you verify. A detailed first evaluation can often tell whether neck or upper-quadrant findings bring on the familiar headache, and whether physical therapy is appropriate. In more complex cases, how you respond over several visits gives more information. If you are in Carbondale or anywhere in Southern Illinois and you want that answer, call us at (618) 243-7822 and we will take a look.
Seek urgent medical care for a sudden “worst headache,” new weakness or numbness, confusion, fainting, seizure, major vision change, or headache with high fever and severe neck stiffness. A medical check is also important for a new or fast-changing headache after an injury or during pregnancy. The same is true after childbirth, or for someone with cancer, a weak immune system or unexplained weight loss. Physical therapy is appropriate once dangerous causes have been ruled out and the exam finds physical contributors we can treat.
Frequently asked questions
Is my headache really just my neck, or is something bigger going on?
Usually it is bigger than the neck. The neck is where you feel it, but the real source is often your whole upper quadrant, the region above a line through the middle of your back at T7, which takes in your upper back, shoulder blades, shoulders, neck, and the base of your skull. Those parts work as one chain, and when the upper back and shoulders stiffen, the neck ends up overloaded and starts referring pain into your head. That is why treating only the sore neck often gives short-lived relief, and why a good evaluation looks at the whole region.
Can physical therapy really get rid of headaches that come from the neck?
For cervicogenic headaches, meaning headaches whose source is the joints and muscles of the neck, yes, often to a large degree. A randomized trial of 200 people found that manipulative therapy combined with targeted exercise reduced both the frequency and the intensity of these headaches, with benefits maintained at twelve months. The hands-on work relieves the current episode and the exercise keeps the load off the structures that were referring the pain, which is what makes the result last.
How do I know if my headache is from my neck or a migraine?
A neck-driven headache is usually one-sided, steady rather than throbbing, starts at the base of the skull, and is set off by neck position or a long day at a screen, with little sensitivity to light or sound. A migraine tends to throb, comes with light and sound sensitivity and sometimes nausea or aura, and runs on its own internal triggers. The two can overlap, so a hands-on neck exam is the most reliable way to sort it out.
Do men and women get these headaches differently?
Yes. Women get them far more often, and they are commonly cervicogenic, coming from a tight upper quadrant carrying years of postural load. Men present with these headaches less often, so a new or persistent headache in a man is worth taking seriously and having a physician check first. It does not mean something is wrong, but because it is less typical, it deserves a closer look before assuming it is only mechanical.
Do I need a referral to see a physical therapist for headaches in Illinois?
Illinois law allows you to be evaluated by a physical therapist without a physician’s referral. Individual insurance plans may still have authorization or coverage requirements, which our office can help you verify.
Why do my headaches get worse at a desk or on my phone?
Holding your head tipped forward forces the small muscles at the base of your skull to work far harder to support it, and it loads the upper-neck joints in a sustained, awkward position. Hours of that irritates exactly the structures that refer pain into the head, which is why screen time and long drives are such common triggers.
We call our approach Whole Body Synergy Techniques: we look at how the whole body is compensating, not only at the spot that hurts. When you are ready to talk it through, call (618) 243-7822, request an appointment online, or learn about the Synergy Healing Program.
About the author. Subrat Bahinipati, PT, is a physical therapist and co-founder of Synergy Therapeutic Group in Carbondale, Illinois, with more than three decades of clinical experience. He treats chronic pain, headaches, nerve conditions and complex muscle and joint problems.
This article is for general education and is not a substitute for individual medical advice. Headaches have many causes; if your headaches are new, sudden, severe, or come with other neurological symptoms, please see a physician promptly. To have your neck and upper back evaluated as a possible source, call Synergy Therapeutic Group at (618) 243-7822.
This article is for medical information and education only. It is not medical advice, and it does not replace an evaluation by your physician or a licensed physical therapist. Every person is different, so please talk to your healthcare provider about your own situation. If you have severe, sudden, or worsening symptoms, or any concern about your health, contact your physician or seek urgent care. Synergy Therapeutic Group, 1110 N Cedar Court, Carbondale, IL 62901, (618) 243-7822.
See more of our articles in Google
If this was worth your time, you can tell Google you want to hear from us. It takes one tap, and it makes our articles more likely to turn up the next time you search for answers about pain, movement, or your child’s development.
