
By Subrat Bahinipati, PT, Physical therapist and co-founder, Synergy Therapeutic Group, Carbondale, Illinois · 30+ years treating chronic and complex pain
Clinically reviewed by Subrat Bahinipati, PT on · Last updated
Key Takeaways
- Your fear is not irrational. Frozen shoulder can be extremely touchy, especially during the painful “freezing” stage.
- Good frozen shoulder physical therapy should match the intensity of treatment to the stage of your shoulder and how touchy it is.
- Cortisone injections can reduce pain for some people in the short term. The response varies, and an injection does not look at the rest of the movement chain.
- Women are affected more often than men. Frozen shoulder commonly appears between ages 40 and 60. Hormones may play a part, but that has not been proven to be the single cause.
- Diabetes is a well-established risk factor. But people without diabetes, surgery, or an obvious injury can also develop frozen shoulder.
- In my clinical experience, the painful shoulder is often only one part of the problem. Thoracic and shoulder-blade restrictions can change how the joint moves, and they should not be ignored.
Physical therapy for frozen shoulder should not mean gritting your teeth while someone forces your arm farther than it wants to go.
Frozen shoulder is painful. Treatment may sometimes cause a mild stretch or short-lived soreness, especially as movement returns. But sharp pain, guarding, or a flare that lasts long after the visit is not something I see as a necessary sign of progress.
If you are afraid treatment will hurt, your fear makes sense. Many patients come to me after experiencing heat followed by aggressive stretching of an already painful shoulder. I do not begin there. I first look at how the thoracic spine, rib cage, shoulder blade, and shoulder are working together. Then I treat the restrictions I find without forcing the painful joint.
Why the Fear of Frozen Shoulder Physical Therapy Makes Sense
Frozen shoulder often begins quietly. There may be no fall, no accident, and no single moment when something went wrong.
At first, the shoulder hurts at night. You wake when you roll onto it. Then reaching behind your back becomes difficult. Putting on a coat, fastening a bra, washing your hair, reaching into a cabinet, or placing your arm under the pillow can become the hardest part of the day.
Medication is often the first step. A cortisone injection may follow. For some people, an injection gives meaningful short-term relief. For others, the change is small or does not last. When physical therapy comes up next, a frightening picture may form. You see a heat pack, then someone pushing a shoulder that already feels as if it cannot take one more thing.
That is where many people stop. They are not refusing help. They are trying to protect themselves from more pain.
I understand that. I have treated too many patients who arrived believing that physical therapy had to hurt before it could help. It does not.
What Frozen Shoulder Actually Is
Frozen shoulder (also called adhesive capsulitis) means the capsule around the ball-and-socket shoulder joint becomes inflamed and scarred. Pain and loss of movement usually progress together, although the pattern and timeline differ from person to person.
Evidence-based guidance for adhesive capsulitis recommends matching treatment to how touchy the tissue is. When the shoulder is very touchy, stretching and mobilization should be nearly pain-free and gentle. Treatment can build as pain settles and tolerance improves. That principle matters. The same force should not be used on every shoulder at every stage.
Where My Approach Differs
The shoulder joint is important, but it does not move alone.
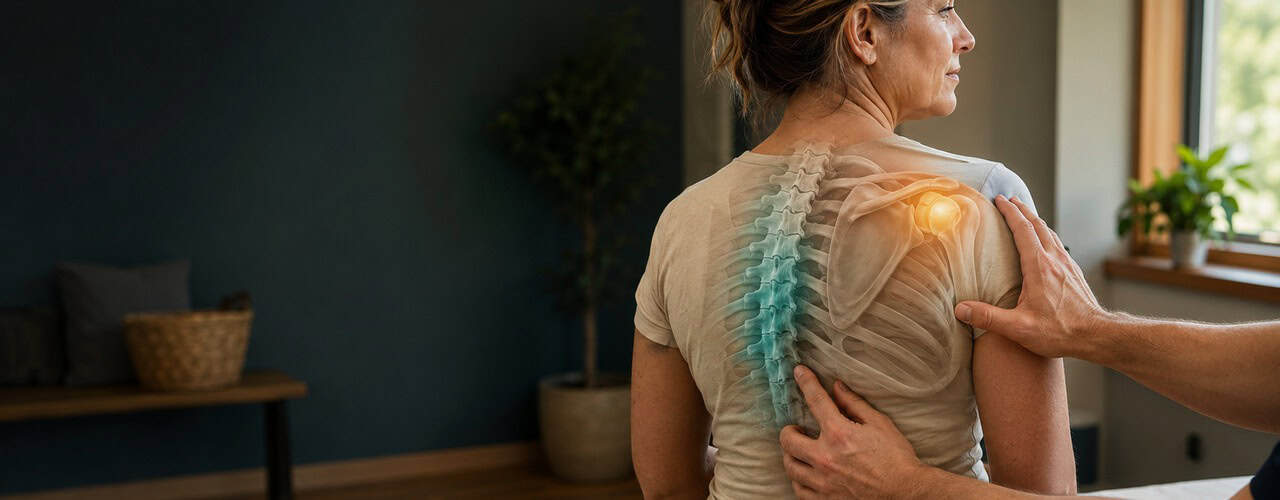
Your shoulder blade rests and glides on the rib cage. The rib cage follows the thoracic spine. If the mid-back is stiff or rounded, the shoulder blade cannot move or steady itself well. Then the ball-and-socket joint has to make up for it.
In more than 30 years of practice, I have repeatedly found meaningful restriction through the middle thoracic region (often near T7) in people who arrive with a painful, stiff shoulder. I do not claim that every frozen shoulder begins at T7. Research has not established one spinal level as the universal cause of adhesive capsulitis. But I do not treat it as a footnote, either. It is the first place I look. In my experience it is very often part of the answer, and ignoring it can mean spending months treating only the place that hurts.
My evaluation asks:
- How is the thoracic spine moving?
- Can the ribs expand and rotate normally?
- Does the shoulder blade glide, upwardly rotate, and stabilize?
- Which movement produces pain, and what changes that movement?
- Is the limitation coming only from the joint capsule, or is the whole chain contributing?
- Are there signs that this is something other than frozen shoulder?
If treating the mid-back or shoulder-blade mechanics immediately changes the way the arm moves, that finding matters. It gives us a starting point that does not require forcing the painful joint.
What I Do Instead of Forcing the Shoulder
I begin with what the body can accept. Treatment may include gentle hands-on work to the thoracic spine, rib cage, fascia, and muscles controlling the shoulder blade. I am trained, along with my co-founder, in the John F. Barnes Myofascial Release Approach, which influences how I address connective-tissue restriction without chasing pain or forcing range.
The sequence is individualized, but it commonly looks like this:
- 1Reduce guarding and restore movement around the thoracic spine and rib cage.
- 2Improve how the shoulder blade moves and stabilizes.
- 3Introduce shoulder motion within the patient’s tolerance.
- 4Build strength and control as pain and irritability decrease.
- 5Return to the specific activities the patient has lost: sleeping, dressing, grooming, reaching, lifting, or working.
This is not simply a “gentler stretch.” It is a different order of treatment.
Here is what I want you to take from that order: when a patient is going through this sequence with me, they are not gritting their teeth through the appointment. That is not luck, and it is not a softer version of the same plan. It is a different plan. A patient may feel pressure or a mild stretch. There may be short-lived soreness as new movement is introduced. But I do not use sharp pain as a target, and I do not judge success by how far I can push an arm during one visit. The goal is movement the patient’s body can keep, not range borrowed for a few minutes at the cost of a long flare. Results differ from person to person, and frozen shoulder is a genuinely painful condition to live with. But the pain that comes specifically from forcing an already unstable joint is not something I ask a patient to endure to get better.
What the Research Supports, and What It Does Not Yet Prove
I believe patients deserve a clear line between established evidence and clinical observation.
Research supports several points:
- Frozen shoulder involves inflammation and scarring of the capsule.
- Treatment intensity should be matched to pain and how touchy the shoulder is.
- Steroid injections can improve pain and function in the short term for some patients. A large systematic review and meta-analysis found the strongest short-term evidence for a steroid injection into the joint. It was usually combined with a home exercise program. That does not mean everyone responds or that an injection addresses every contributing movement problem.
- Diabetes raises the risk a lot. A meta-analysis estimated adhesive capsulitis in about 13.4% of people with diabetes. It found that people with diabetes were approximately five times more likely to develop it than controls.
- Manipulation under anesthesia works by forcefully breaking up the tight capsule. An arthroscopic study has documented capsular tears and, in some cases, injury to other structures. Doctors usually consider it only when good conservative care has not helped enough. It is not an automatic next step.
Research has not proved that every frozen shoulder begins in the mid-back, that one posture causes it, or that falling estrogen alone explains it. Those claims would go beyond the evidence.
What I can say is that frozen shoulder is more common in women and often appears around the time of menopause. A 2026 pilot study of 1,952 menopausal women found adhesive capsulitis in 7.65% of those not using hormone therapy and 3.95% of those using it. But the difference was not statistically significant. It is an interesting signal, not proof that hormone therapy prevents or treats frozen shoulder.
That distinction matters. Patients deserve to know what has been established, what is still being studied, and what comes from one clinician’s experience. I would rather tell you what I actually know than dress up a guess as certainty. Here is what thirty years in the clinic have shown me. When I treat the mid-back and shoulder blade first, patients get relief without the joint being forced. That has held up, even though science has not fully pinned down why this happens to so many healthy women.
What Catching It Early Looked Like
A patient came to me recently: a researcher in her fifties at a university. She had a few months of mild, nagging shoulder pain that suddenly turned severe, with no injury and no explanation. Her primary care doctor offered pain medication. Her work demands precision, and she did not want anything that would cloud her thinking, so she declined. They talked about an MRI, then changed course toward an orthopedic referral instead, and that referral was two to three weeks out.
She did not want to spend two to three more weeks in that much pain, so she used direct access and called us on a friend’s recommendation.
On exam, the signs were textbook: tenderness in the joint, a painful limit in one specific direction, and tenderness right at T7. I told her plainly what I tell every patient in her position. This is very common. It is not life-threatening. An MRI at this point was unlikely to show much of anything.
She was in the acute stage, not yet the frozen stage, and her pain was severe enough that scapular mobilization on its own was not going to be a comfortable place to start. So I taped her scapula to stabilize it (a small, low-force step, not a stretch and not a force) and her pain dropped noticeably within twenty-four hours. Partway through treatment she mentioned she had also been living with neck pain for a long time. It is the same upper quadrant, so we treated that too.
In under six weeks, she never progressed to the frozen stage at all. That is the part that matters most. If this gets left alone, the frozen stage is where it becomes genuinely difficult: for the patient and for treatment. Catching it early, before the joint locks up, changes the entire course. She eventually had an MRI on her own; it came back with nothing significant. She told me afterward that I had been right from the start.
Identifying details changed. Individual results vary and are not a promise or prediction of another patient’s outcome.
You Do Not Have to Choose Between Living With It and Being Hurt by Treatment
Frozen shoulder can take over sleep, dressing, work, and the small movements most people never think about until they lose them.
You may have been told to wait a year or more. You may have tried medication or an injection. You may have already had painful therapy. None of that means you should be forced through the same experience again.
A careful evaluation should find what is actually limiting you, how touchy the shoulder is, and where treatment can safely begin. At Synergy, that means looking beyond the painful joint while still respecting what is happening inside it.
If fear of pain is the reason you have delayed physical therapy, tell us before your first visit. We will listen.
You do not have to be forced through treatment to get relief.
Illinois law allows a physical therapist to provide services with or without a referral, although insurance-plan requirements vary.
Related reading: Frozen shoulder and adhesive capsulitis · Shoulder pain treatment in Carbondale · What to expect on your first visit
Frequently Asked Questions
Does physical therapy for frozen shoulder have to hurt?
No, and I mean that plainly: as a physical therapist treating frozen shoulder in Carbondale, I do not have my patients gritting their teeth through a session. Mild stretching or temporary soreness can occur, but sharp pain and prolonged flaring are not proof that therapy is working; they are usually a sign that force is being aimed at the wrong place. Treatment should be matched to the irritability and stage of the shoulder, then progressed as tolerance improves. Results vary from person to person, but the pain that comes from forcing an unstable joint is not something I ask a patient to endure.
Can aggressive stretching make frozen shoulder worse?
An overly aggressive session can increase pain, guarding, and post-treatment irritability, especially during the painful freezing stage. That does not mean all stretching or joint mobilization is harmful. The dose, timing, direction, and patient response matter.
I already tried a cortisone injection. What should I do next?
An injection can provide short-term relief for some patients, but response varies. If pain or stiffness continues, the next useful step is a full evaluation of the shoulder capsule, shoulder blade, thoracic spine, strength, movement pattern, and functional limitations. Repeating an injection or choosing another procedure is a decision to make with your physician.
Is frozen shoulder caused by menopause?
Not proven. Frozen shoulder is more common in women and frequently occurs between ages 40 and 60, which overlaps with perimenopause and menopause. Early research suggests hormones may be involved, but current evidence does not establish declining estrogen as the single cause or hormone therapy as a treatment.
Is diabetes connected to frozen shoulder?
Yes. Diabetes is one of the strongest established risk factors. People with diabetes are more likely to develop frozen shoulder, although many people with frozen shoulder do not have diabetes.
What happens at the first visit?
The first visit at Synergy Therapeutic Group in Carbondale is an evaluation, not a test of how much pain you can tolerate. We review how the problem began, sleep disturbance, health history, previous treatment, and the activities you have lost. We assess the neck and thoracic spine when relevant, shoulder-blade mechanics, active and passive shoulder motion, strength, and symptom response. Treatment begins from those findings, not from a one-size-fits-all protocol.
How soon will I notice a difference?
There is no honest universal timeline. It depends on irritability, duration, health conditions, previous treatment, and how the shoulder responds. Some patients notice an early change in pain or movement; others progress more gradually. An evaluation provides a better estimate than the diagnosis alone.
When should shoulder pain be medically evaluated promptly?
Seek prompt medical attention for pain after significant trauma, visible deformity, sudden weakness, chest pain or shortness of breath, fever, redness or warmth around the joint, numbness or progressive neurologic symptoms, or signs of infection. Those findings are not something to assume is frozen shoulder.
Your body is not broken, it is adapting. We call our approach Whole Body Synergy Techniques: we look at how the whole body is compensating, not only at the spot that hurts. When you are ready to talk it through, request an appointment online or learn about the Synergy Healing Program.
Subrat Bahinipati, PT is a physical therapist and co-founder of Synergy Therapeutic Group in Carbondale, Illinois. He has more than 30 years of clinical experience and training in the John F. Barnes Myofascial Release Approach.
This article is for medical information and education only. It is not medical advice, and it does not replace an evaluation by your physician or a licensed physical therapist. Every person is different, so please talk to your healthcare provider about your own situation. If you have severe, sudden, or worsening symptoms, or any concern about your health, contact your physician or seek urgent care. Synergy Therapeutic Group, 1110 N Cedar Court, Carbondale, IL 62901, (618) 243-7822.
See more of our articles in Google
If this was worth your time, you can tell Google you want to hear from us. It takes one tap, and it makes our articles more likely to turn up the next time you search for answers about pain, movement, or your child’s development.
